

Radiation oncology resident @MSK_RadOnc | PGY-1 @newtonwellesley @MassGenBrigham | MD @GeiselMed @dartmouth | Married to @AlexaRiobueno | He/him
MSKCC via Dartmouth/Broad/BU
Joined August 2012
- Tweets243
- Following568
- Followers461
- Likes470



Pinned Tweet
Excited to share our new paper with @Mitch_P and @Luke_Pike_MD @pike_lab!
Nearly 4,000 brain mets patients treated with linac-based SRS at MSK: contemporary survival outcomes, prognostic factors, and what happens next with salvage treatment. 🧵
doi.org/10.1093/noajnl/vdag2…

Drew T Bergman, MD retweeted

I read with interest the article by Madani et al about dose-painted spine SBRT and targeting of GTV or a segment-based approach.
TL;DR: These results are intriguing, but I prefer not dose-painting based on the strength of our results @MSK_RadOnc, and I strongly advise treating the entire at-risk volume electively as per the international guidelines. We have published ample data that this approach results in durable local control with very low risk of adverse effects.
redjournal.org/article/S0360… 1/

Drew T Bergman, MD retweeted

Pleasure to have a colleague notify me today that our article is in print in the @JCO_ASCO
"Prognostic and Predictive Effect of Age in Molecularly Defined Lower-Grade Gliomas"
ascopubs.org/doi/full/10.120…

Drew T Bergman, MD retweeted

Have you ever looked at a gene in IGV or a genome browser and wondered “What are all those (ATAC-seq/H3K27ac/CTCF ChIP-seq/…) peaks doing?” 🤔 I’m thrilled to share that we developed a new technology called Swap-seq to answer that exact question.
biorxiv.org/content/10.64898…

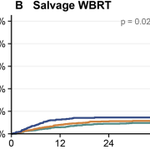
What happened after SRS?
Salvage WBRT was uncommon. Among patients without prior WBRT, 24-month cumulative incidence was:
• 1 lesion: 4.5%
• 2–4: 5.5%
• ≥5: 7.3%
Risk increased with burden, but absolute use remained low, accounting for competing mortality.

1
2
179
A huge team effort: thank you to our co-authors and teams across all 7 sites!
@hswalch @brandon_imber @Chris_JacksonMD @RadOncConnor @JohnCuaron @jjnaylor02 @theRADSofKHAN @DYerramilli_MD @yaoyu_md
1
4
159
Evidence for upfront SRS with higher lesion ceilings is mounting, an approach we've favored over WBRT for years @MSK_RadOnc.
We assembled 3,893 consecutive patients across 7 sites from 2017–2026, to our knowledge the largest contemporary linac-based SRS cohort reported to date.
1
2
389

For 11–20 vs 5–10 lesions, adjusted HR was 1.04 (95% CI 0.86–1.27), meeting the 1.30 non-inferiority margin in a post hoc analysis.
Beyond 20? Still an open question. Only 41 patients, and non-inferiority was not established. More to come!

1
1
164
Building on Yamamoto et al and others, we found a familiar pattern in the modern systemic-therapy era and in a more diverse group of cancer types beyond NSCLC: survival plateaued from 5–20 lesions.
Median OS:
• 1: 16.2 months
• 2–4: 11.0
• 5–10: 8.2
• 11–20: 8.7

Drew T Bergman, MD retweeted

Thrilled to publish the results of the ROADS trial for newly dx’d brain mets requiring surgery. The results define a new standard. Congrats Dr. Beckham and all co-authors! @jco_asco
@UTMDAnderson @ASCO #oncsurgery ascopubs.org/doi/10.1200/JCO… @NSTumorSection

Drew T Bergman, MD retweeted

📜 In @JNCI_Now, we present "A phase II randomized study of proton therapy vs intensity-modulated radiation therapy in patients with unilateral head and neck cancer"
Thank you Drs @imrtlee @xrtGenomics & team @MSKCancerCenter @MiamiCancerInst @MayoRadOnc
pubmed.ncbi.nlm.nih.gov/4269…


🔵 Phase 2 (n = 98)randomized trial of proton beam RT vs IMRT in postoperative unilateral #HeadAndNeckCancer
➡️ Clinician-graded grade ≥2 mucositis 7.4% vs 22.7% (P=.03), dysgeusia 9.3% vs 31.8% (P=.005).
🔗: oxford.ly/4Ay4H9V
@IMRTLee | @xrtGenomics | @EChrisDee
Drew T Bergman, MD retweeted

Important data from the UK HEAT and ICE registries on focal therapy for localized prostate cancer—and an important discussion about what these data can (and cannot) tell us.
Our response in @EUplatinum 👇
sciencedirect.com/science/ar…

Drew T Bergman, MD retweeted

Big news for Radiation Oncology @WilmotCancer: Dr. Jacob Scott (@CancerConnector) joins our faculty this fall. A physician-scientist who uses math and modeling to personalize the dose for each patient and each tumor. Our team is growing. @UR_Med #RadOnc #CancerCare
New preprint!📄 medrxiv.org/content/10.64898…
RT dosing in locally advanced rectal cancer (LARC) is empiric, a few trial-derived schedules applied uniformly, not reflecting the individual tumor's biology.
Does a pretreatment genomic estimate of radiation effect track outcomes? 🧵

Big thanks to @DrPaulRomesser @CancerConnector @MSK_RadOnc, our entire colorectal DMT here at @MSKCancerCenter for their willingness to collaborate on this, @JoshSmithMDPhD, and also our German colleagues at the CAO/ARO/AIO group (Emmanouil Fokas + Claus Rödel).
See additional recent work (from GARD working group) taking this framework to the next step to one day benefit patients:
in HPV+ H&N cancer:
jci.org/articles/view/194073
in peds CNS cancer:
medrxiv.org/content/10.64898…
and translating RSI to the NGS era:
biorxiv.org/content/10.64898…