

Pathologist 🔬🇧🇷 Opinions are my own. “Things should be made as simple as possible, but not simpler.” A.E.
Joined April 2018
- Tweets2.2K
- Following980
- Followers1.6K
- Likes6.4K




Jackson Barbosa, MD retweeted

Excited to share our team's recent study on a long-puzzling issue in lung carcinoids/NETs.
So many “aha” moments when working on it! Happy to share the lessons we learned both for the diagnostic approach & very interesting underlying biology.
modernpathology.org/article/…

Jackson Barbosa, MD retweeted

The #Parasite Case 820 is up, a subcutaneous nodule in a man from Liberia. Check out the whole slide image to make your diagnosis! parasitewonders.blogspot.com… 🪱
Answer later this week. #mayopath #pathology #PathBugs #CrittersOnTwitter


Not a routine double stain but a reassuring one in selected cases.
CyclinD1/CD138 highlights the very few abnormal plasma cells in this bone marrow. This was one the only areas they could be found.

Jackson Barbosa, MD retweeted

Sharing a rare/hard case for the #hemepath enthusiasts. This presented in a young adult.
Hint: note the pattern of involvement. I'll be sharing a few stains throughout the next few days.


Jackson Barbosa, MD retweeted

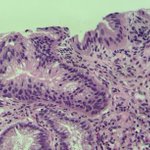
H.pylori in Duodenum 🗒️
H. pylori is rarely seen in duodenal biopsies (usually 0–5%, ~2% on IHC), only on gastric metaplasia
But H. pylori gastritis drives a large share of duodenitis:
• ~50–60% of histopathologic duodenitis
• Often higher (70–90%) in active/acute cases
Always check the stomach when you see active duodenitis. In this case, gastric biopsy was positive for Helicobacter IHC.
Pics: Duodenitis, left. Helicobacter IHC, right
#GIpath #pathology #PathX #pathtwitter


Jackson Barbosa, MD retweeted

Another classic "KIT"fall - metastatic melanoma presenting as a gastric polyp. Melanomas often express KIT/CD117.


Jackson Barbosa, MD retweeted

Out today @SpringerNature … our latest on CMML 🚨
Because life would be boring without a little bit of (diagnostic) controversy 😉
rdcu.be/fxyod
Rob and I hope you enjoy reading this as much as we did writing it.
#hemepath

Jackson Barbosa, MD retweeted

This is a gastric mucosal biopsy: The clue to this "one stain diagnosis" is that GISTs seldom involve the mucosa.
Ortiz Requena D, et al. Synovial Sarcoma of the Gastrointestinal Tract. Mod Pathol. 2024 Jan;37(1):100383. PMID: 37972927.


Jackson Barbosa, MD retweeted

There is currently an outbreak of Cyclospora in the USA. Has anyone seen a case recently? These photos are from a case that @RhondaYantiss kindly shared with me several years ago. #pathology #PathTwitter #PathX #gipathology #crittersontwitter


Ki67 (MIB1) is an EXCELLENT benchmark to evaluate how aggressive decalcification was. MPO (left) / Ki67 (right). Hematopoiesis should show ⬆️ Ki67. This is especially valuable for external samples. Do not interpret other antibodies unless you see internal controls for each.


I’m not a #cytopathology person but I deeply appreciate the level of details it reveals.
Longstanding nodule in adult male. Intraoperative analysis for surgical margin evaluation.
Paraffin dx: Typical Carcinoid Tumor.


Low grade dysplasia.
Single tiny focus.
I only saw it after p53 🫠
Do you do p53 in every Barrett’s Esophagus biopsy?
Is it too much? Idk. But sometimes I feel us pathologists hesitate over a few stains while batteries of labs and imaging go unquestioned.


Jackson Barbosa, MD retweeted

Very cool! #Pathbugs #crittersontwitter

So excited to share that our new review article is now online in Diagnostic Histopathology!🎉
📝 “Recognizing parasitic helminths in tissue: histopathological insights into fascioliasis and echinococcosis” 🔬
authors.elsevier.com/a/1nQPh…
#pathology #histopathology #echinococcosis


Jackson Barbosa, MD retweeted

Pathologists! When was the last time you saw a splenectomy for hairy cell leukemia? Here’s a classic case. #hairycellleukemia #hematopathology #spleen – at Boston, MA


Dear #hemepath people! Has anyone seen this before? Child with recent PVB19 infection (few weeks). Now LAD showing reactive hyperplasia. PVB19 IHC below. No nuclear staining.
Is it plausible this represents trapped virions/immune complexed capsid like p24? Or just non specific?


