

Cardiologist - Echocardiography- 🇧🇷
Brasil
Joined April 2014
- Tweets545
- Following1K
- Followers594
- Likes2.3K



Pinned Tweet
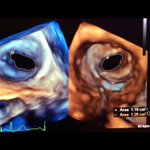
Carpentier's Classification - Severe Mitral Regurgitation Type IIIb. Systolic leaflet restriction of posterior leaflet secondary evolved inferior STEMI.
roberto waltrick retweeted

Volumetrics deliver a quality check and shine✨especially in eccentric regurgitation. #echofirst @NMerke
⭕️ RVol AR = LVOT SV - RVOT SV
👉 RVol AR = 132 - 70 = 62 ml
⭕️ RFr AR = RVol AR / LVOT SV
👉 RFr AR = 62 / 132 = 46%


roberto waltrick retweeted

🫀 The mechanism: RCC prolapse (Type II AR).
🔍 The key finding is a transverse fold, giving the cusp a “broken valve” appearance.
👀 3D en-face view: transverse fold.
2D long-axis (Flexi-Slice white plane): characteristic “W sign”.
Two views of the same mechanism!

🫀 Aortic regurgitation on 2D/3D TEE.
An incidental finding during TEE before cardioversion.
What is the underlying mechanism of AR 🔍
👇 Poll below
#EchoFirst #CardioTwitter
roberto waltrick retweeted

If we want to achieve regression of atherosclerosis, we need to lower LDL to <55 and even better, <40. Need to better explain to patients the benefits of intensive LDL lowering @AHAScience

roberto waltrick retweeted

Cut it out! In obstructive HCM, adding surgical cutting of thickened, retracted secondary chordae of the anterior mitral leaflet to septal myectomy delivered excellent long-term clinical & hemodynamic results. #JACC @A_sorropago
More: bit.ly/4zjCAKF

roberto waltrick retweeted

Updated intro2echo.com with sections on structural heart echo.
Walks through the steps for TAVR, mTEER, and tTEER. This includes 3D models as well as simulated 2D ultrasound images.
Would appreciate feedback and suggestions for improvement!
intro2echo.com/#mteer
roberto waltrick retweeted

Rare congenital anomaly(I’ve never seen)
rudimentary aortic chordae tendineae #echofirst
seen as ruptured fibrous strand attached to RCC free edge w partial flail causing severe aortic regurgitation OR confirmed bit.ly/3ULiWIb
roberto waltrick retweeted

My #echofirst Approach to PISA EROA in Mitral Regurgitation: A Critical Review doi.org/10.36660/abcimg.2024…

roberto waltrick retweeted

🫀My Approach to Echocardiographic Assessment of Left Ventricular Filling Pressures: From Ambiguity to Precision With New Guidelines @DICSBC #echofirst #cardiology #diastolic
🔗 abcimaging.org/wp-content/up…

roberto waltrick retweeted

PVC localization has been one of the harder things to learn and teach as a cardiology fellow interested in EP.
So I built learnpvcs.com to help connect the 12-lead ECG with 3D cardiac anatomy.
You can explore different PVC origins, rotate and look inside the heart, and work through practice cases.
It's an early educational prototype, and I'd love feedback from fellows, electrophysiologists, and educators.
Which PVC origin do you find hardest to localize?
#CardioTwitter #EPeeps #MedEd @OpenAI @WvuCvFellows @wvudeptofmed

roberto waltrick retweeted

🫀 Case: F, 64y.o., metastatic lung adenocarcinoma
🧠 Cerebral emboli despite full-dose apixaban
🔎 TTE: irregular, verrucous appearance of the leaflet edges, impaired coaptation
➡️ A classic #NBTE -Nonbacterial thrombotic endocarditis- constellation #MaranticEndocarditis
High CRP is common in advanced cancer and ≠ IE
Nevertheless, IE must be excluded with blood cultures 🧫 and the overall clinical picture
roberto waltrick retweeted
A short educational hook🪝on the aortic complex: What do we actually measure on intraoperative TEE? And when?🫀#echofirst
Bonus: histology🔬


roberto waltrick retweeted
Normal Coronary Artery Origins 🧭
📌 TEE 🆚 TTE
📌 ME AV SAX 🆚 PSAX
📌 💛 versus 💚
📌 counterclockwise 🆚 clockwise
#echofirst
*NF = non-facing sinus

👉🏻Leiden: sinus 1 (Right facing RCA) and sinus 2 (Left facing LCA)
👉🏻Shaher 1 (Lessons Learned from Prof. Takigiku 🇯🇵)
@AEPCcongenital @ASE360 @escardio
@iamritu @CASivaram1 @loomba_rohit @alex1708ander @CardioNeo @SIwa23288585 @WithAScalpel @echoleolopez @swatigar @sujithsp
roberto waltrick retweeted

Premature xanthelasmas (XP) in a healthy 37 year old female with a LDL of 107mg/ml, lipid profile including Lp(a), thyroid panel are normal. Very strong family history of premature ASCVD Any advice on additional workup is appreciated. Advanced genetics and sterol balance workup is pending.
Normolipidemic XP is usually idiopathic/local, but it still warrants a complete metabolic workup and cardiovascular risk assessment. Atypical or extensive periocular xanthomatous lesions should prompt consideration of NXG, Erdheim–Chester, AAPOX, and paraproteinemia rather than being dismissed as “just xanthelasma with normal cholesterol.”

roberto waltrick retweeted
Volumetric approach in MR 🎯
This represents a much-needed change in approach 🌟 (🆚 PISA)
Step 1 - calculate LV SV = total stroke volume
Step 2 - calculate LVOT SV = forward volume
Step 3 - calculate RegVol MR = LV SV - LVOT AV
Step 4 - calculate RF MR = RegVol MR/LV SV


roberto waltrick retweeted
We all struggle to understand severity quantification of regurgitation by #echofirst If our KOL present cases on the big stage they show severe Regurgitation showing VC width or 3DVCA usually without showing the needed machine settings We need to understand how to do #EACVI26

roberto waltrick retweeted

Anticoagulation across the CKD spectrum, from ESC 🫀💊
eGFR 30-59: DOAC preferred over VKA/LMWH (Class I) — for both VTE & AFib
eGFR 15-29: Factor Xa inhibitor preferred (Class IIa for AFib, IIb for VTE)
eGFR <15/dialysis: VKA, low-dose apixaban, or low-dose Factor Xa inhibitor

roberto waltrick retweeted

🫀New @escardio Heart Failure Guidelines! 🙌🏻
Full article here: escardio.org/guidelines/clin…
Key takeaways 👇🏼
#HeartFailure #Cardiology #ESC2026
🤖 Made with AI

roberto waltrick retweeted

How low should we go with BP in atrial fibrillation?
Our #ESC2026 study, simultaneously published in @EuropaceEiC , suggests a “sweet spot”:
🔹 SBP ~120–130 mmHg
🔹 Avoid DBP <75–80 mmHg
🔹 Lower is not always better
In AF, both numbers matter.
bit.ly/4yeNyQB
#AtrialFibrillation #Hypertension
@ElnazShmohamadi @melissaemm1 @Elliott_AD @JonathanAriya

roberto waltrick retweeted

🚨 The 2026 @escardio #HeartFailure Guidelines are here❗️#ESCcongress @secardiologia
1) HFmrEF is gone.
Acute HF is gone.
NT-proBNP cut-offs are now age-adjusted.
Everything that matters 🧵👇
2/ 🔄 NEW DEFINITION — two phenotypes only
❤️🩹 HFrEF → LVEF <50% + symptoms/signs
🫀 HFpEF → LVEF ≥50% + symptoms/signs + objective evidence of structural/functional abnormality
❌ HFmrEF eliminated: same aetiology, same pathophysiology, same treatment response as HFrEF
