
lefty web and games developer and besmircher of all things lacking in pancake-based characteristics he/him
UK
Joined May 2009
- Tweets1K
- Following586
- Followers148
- Likes19.4K





Mike retweeted

The NHS accept they've seen significant growth in demand since COVID. They say they've looked at everything but still can't say for definite what the cause is, only that we should assume it's here for the foreseeable. That was September's data, so maybe October had more clues? 😷


Mike retweeted

Long-COVID: Ultrasensitive multiplex protein biomarker profiling reveals subclinical neuroinflammatory and innate immune dysregulation without correlation to symptom severity
🚨LongC0VID patients show a hidden cytokine-storm + neuroinflammation signature that only ULTRA-SENSITIVE PROTEOMICS can detect. Yet the biology doesn’t match how sick they feel. The real driver may be central sensitisation or brain rewiring.🤔
➡️Very interesting small Norwegian study, bear with me!
- Routine labs are normal in longC0VID, yet patients have persistent fatigue, cognitive issues, depression, and other symptoms more than a year after infection.
- In this matched case-control study (48 longC0VID patients vs 48 fully recovered controls, median ~65–72 weeks post-infection), ultrasensitive NULISAseq proteomics (123 CNS/immune biomarkers at attomolar sensitivity) detected clear biological differences invisible to standard tests.
- 19 proteins were significantly dysregulated; top upregulated markers included CCL22, IL-6R and CST3. Pathway analysis showed activated Pathogen-Induced Cytokine Storm, Neuroinflammation, and IL-10 signalling pathways, pointing to low-grade innate immune activation and neuroinflammatory signals.
- Hierarchical clustering split longC0VID patients into two biological subgroups (one dominated by metabolic reprogramming/mitochondrial dysfunction and cytokine-storm features, the other by neuroinflammation and related signalling).
- Critically, neither the protein levels nor the biological clusters correlated with symptom severity, fatigue, depression, cognitive scores, or any patient-reported outcomes. Conventional PCA also showed no clear patient-control separation.
- The study does not examine reinfection or vaccination status. It simply compares people with ongoing longC0VID symptoms versus people who fully recovered, both more than one year after documented SARSCoV2 infection.
➡️The authors conclude that subclinical immune/neuroinflammatory dysregulation is present but does not map directly onto how sick patients feel, implying additional mechanisms (central sensitisation, epigenetic changes or similar) convert peripheral signals into the clinical picture.
‼️So, according to these authors, LongC0VID harbours a real but hidden biological footprint of innate immune activation and neuroinflammation that standard medicine cannot see and that does not match the intensity of patients’ symptoms, pointing to brain-level amplification mechanisms as the missing link.
‼️Important take-away:
1. For the millions still living with longC0VID, this matters because it shows why ordinary blood tests are repeatedly “normal” while people remain disabled. It validates that low-level immune and neuroinflammatory changes can persist >1 year and explains the frustrating mismatch between lab results and lived experience. Clinically it argues against relying solely on symptom scores or standard inflammatory markers for diagnosis or trial endpoints, and it supports research into treatments that address both residual immune signalling and central sensitisation/pain-processing pathways. It also reinforces that longC0VID is heterogeneous at the molecular level even when symptoms look similar.
2. Finally, this study doesn’t contradict earlier ultrasensitive findings, actually, it confirms and extends them. The attomolar view of longC0VID as a state of low-grade, heterogeneous innate immune and neuroinflammatory dysregulation that is largely invisible to routine labs and poorly linked to symptom intensity is holding up across platforms and other cohorts.
We’re getting somewhere!
#AvoidSars2 #AvoidReinfection
nature.com/articles/s41598-0…

Mike retweeted

Hi everyone, we’ve been working on something 🙏🏼 I’ve written a second letter to Andy Burnham, alongside 360 sports people, to urge him to meet with me and fund research into my much neglected health issue which impacts millions of others.
I can’t believe 360 people signed in just 1 week, so many amazing names and messages still coming in of people wanting to add theirs (so feel free to message to add yours, we’re keeping on the pressure!!!)
The list includes 114 Olympians, with 77 medals between them (and that’s not even including Worlds and Europeans 🤯). Also some huge names from football and many other sports!!
Thank you SO much to everyone that signed, I can’t tell you how much it means to me when I’m truly at rock bottom ❤️❤️❤️
I know everyone wants their issues taken seriously, but this has been neglected like nothing else. WE HAVE 0 APPROVED TREATMENTS!!! Please listen 🙏🏼 @andyburnham @number10gov @UKLabour @DHSCgovuk


Mike retweeted

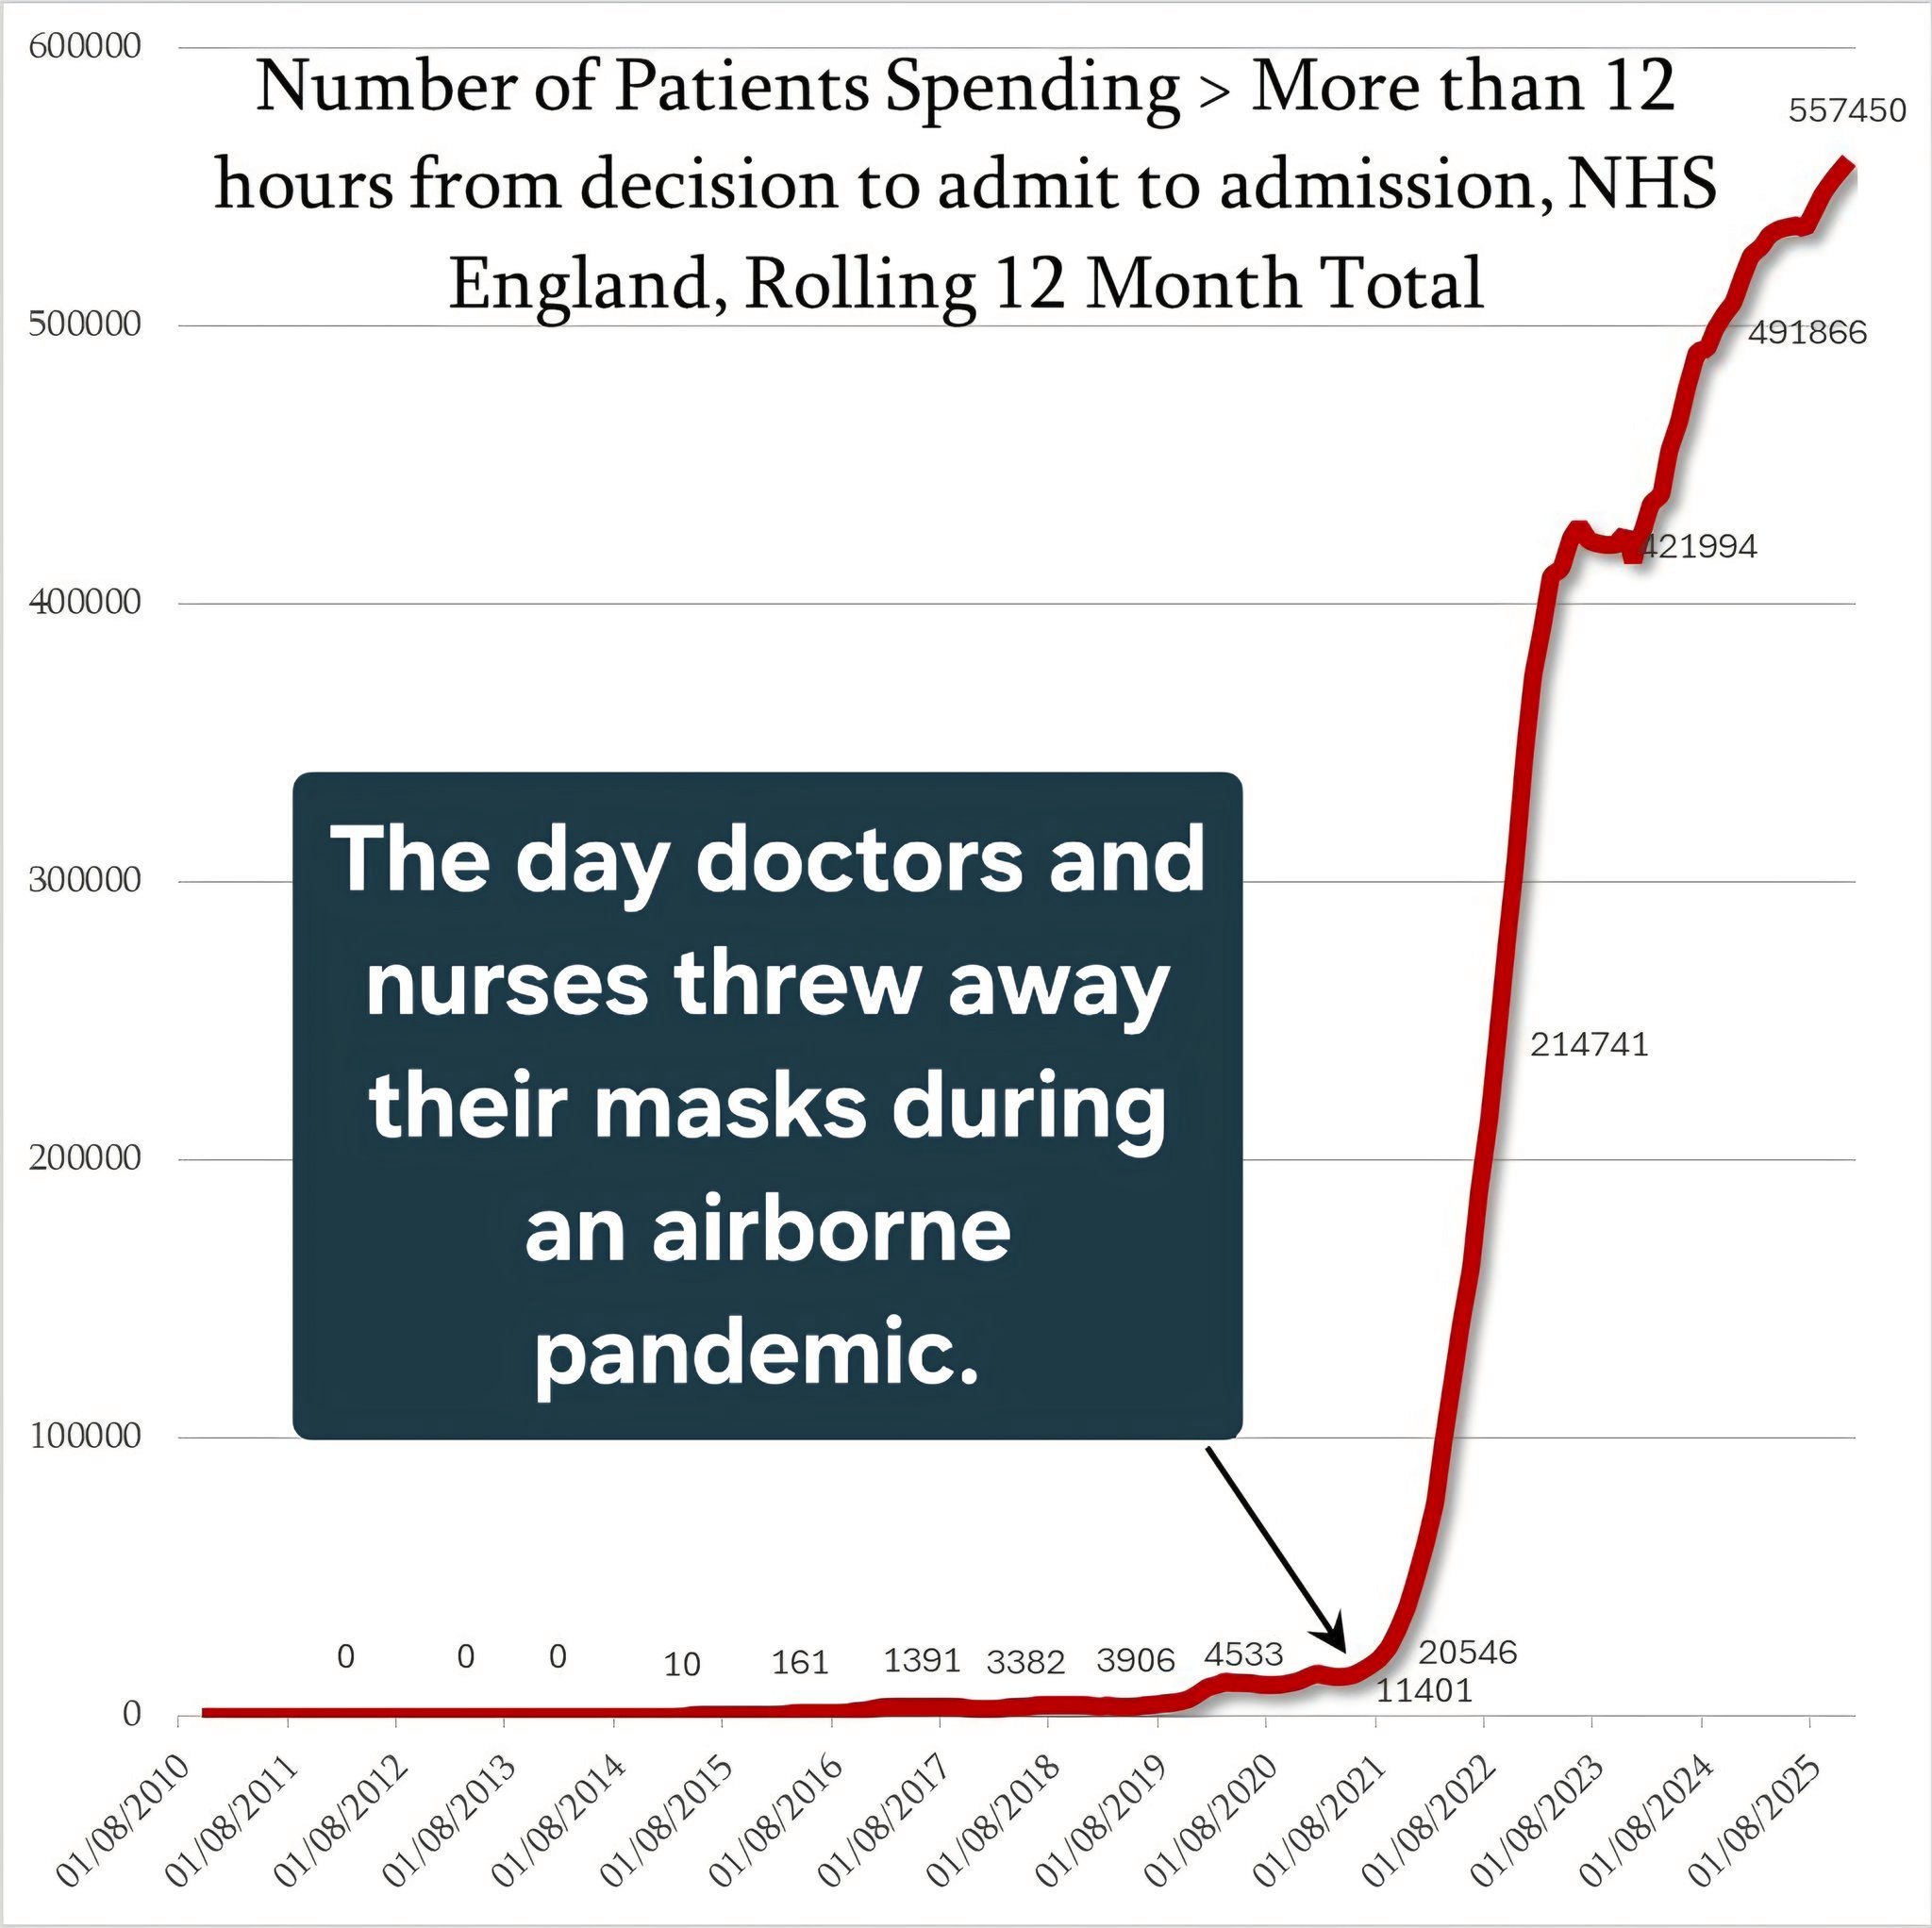
Doctors, nurses, all healthcare workers I beg you - please wear a mask at work.
Be a role model.
My neighbour sat through a heart attack rather than go to hospital and catch Covid from the staff and die, as my husband did.
Mike retweeted

My report has now been published!
- Just under 70% of those surveyed are at least housebound due to their chronic illness. Over a quarter are bedbound or hospitalised.
- Yet, 92.0% of respondents were no longer under the monitoring or care of any NHS specialist department, and 72% were no longer under primary care (GP) monitoring.
- 88.9% of bedbound participants with "contested" conditions are too ill to access face-to-face NHS care at all, with no adaptations and appropriate travel arrangements being facilitated so they can get the help they need – which is rarely available within the NHS.
This doesn't even scratch the surface of the shocking revelations I encountered through this research.
Forced to Go Private is now live, with voiceover available. As always, this is free of charge. (Link in first reply.)
I don't usually ask this, but shares of this report would be extremely useful, so it doesn't just remain within our echo chamber. Therefore, please consider retweeting or passing the link on. This is a scandal and is completely unsustainable, both for patients and the handful of private services who are able to offer at least some of the help we need.
Thanks once again to the amazing volunteers who took part in this survey, despite being in such poor health. I truly hope this does you justice and that together we can make change. 💚
#NHS #longcovid #dysautonomia #MCAS #MECFS #EDS #vaccineinjury #PAIS #POTS #lyme #scandal #medicalgaslighting

Mike retweeted

Hi Leo, greetings from Australia. I'm an anaesthetist, and I wear an N95 mask in all shared indoor air to protect my patients, my community, and myself. I also educate my fellow doctors about the science: covidfordoctors.org
You’re unable to view this Post because this account owner limits who can view their Posts. Learn more


Mike retweeted

Five years ago, Beth Dobbin was an Olympian
Today, ME leaves her in bed 22 hours a day
Even this interview could cost her months of health
But she spoke anyway, because millions are suffering in silence, and she knows her voice might help them be heard
bbc.com/sport/athletics/arti…

Mike retweeted

Our Psychologisation infographic is out!
By coincidence, The Guardian published an article today reporting that women with autoimmunity are 74% more likely to be told their symptoms are psychological than men. Psychologisation is still a huge problem in medicine.
Our article & The Gs 🖇️👇️

ALT Long Covid Advocacy infographic on psychologisation, with pastel boxes, icons, and text on harms, myths, and evidence-based care.
Mike retweeted

I’m appalled that the R word is returning. Listen to disabled people when we tell you that this word is offensive and rude. There’s absolutely no reason to use that word. We’ve made progress with this and it’s going backwards. Please stop using that word!

Mike retweeted
Pretty devastated to have become officially unemployed due to severe and incurable sickness, at the age of 35.
For all those ghouls out there, I continued to work from bed until I was briefly hospitalised with dangerous heart rhythm changes during an autonomic crisis in April 2025, after having been ill since a mild COVID infection in 2021.
As everyone who knows me is aware, things drastically deteriorated from that hospital incident, leaving me almost completely bedbound and reliant on full time care.
No wedding. No children (apart from Rocky the cat) No job. No economic activity.
My NHS GP is an absolute diamond and has finally secured my bedbound status so I can get some the basic blood tests and injections I need at home. She's also taken on all the private specialists' prescription requests and never once asked me if I'd considered getting some sunlight and going for a walk.
However aside from her, the NHS does not give a F***. The government does not give a F***. The media does not give a F*** (apart from George Monbiot and less than a handful of others)
My question is therefore simple.
HOW DARE THEY COMPLAIN ABOUT SICKNESS RELATED ECONOMIC ACTIVITY WHEN WE ARE SCREAMING OUT FOR HELP TO GET BACK TO WORK??
Mike retweeted

I am no longer a registered nurse.
Not through any choice, but because I got #LongCovid.
2 years ago I lost my nursing job because I'm too ill too work. Today my nursing registration expired.
20+ yrs given to the NHS. Ended by getting a disease without a cure.


Mike retweeted

“Can I do it?” is a terrible measure of disability.
Yes, I can do it.
Can I do it repeatedly?
Can I do it safely?
Can I do it without support?
Can I do anything afterwards?
Can I do it tomorrow too?
What does doing it COST?
These tell me a lot more about my capability.

Mike retweeted

So it seems there's a misconception on here that Covid informed folks are asking for extreme mitigations or societal-wide closures to prevent long COVID. Most of us just want *any* mitigations. Opening a window or asking doctors to mask for their ER shift isn't a lockdown


Mike retweeted
Can't share it enough! Article in full:
theguardian.com/commentisfre…
